
Assessing the role of commercial complementary foods in children's diets in Kenya and Bangladesh

Background

Children and caregivers everywhere deserve access to affordable, healthy, and nutritious food. While homemade foods remain central to young children’s diets, the reality is that many families are also choosing commercial complementary foods (CCF), and they have a right to products that are safe and nutritionally appropriate.

Healthy Starts is a research initiative exploring how CCF are shaping the diets of older infants and young children in Kenya and Bangladesh. While wasting, stunting, and micronutrient deficiencies remain major nutrition challenges among children under five, childhood overweight is also emerging as a concern, reflecting the growing double burden of malnutrition. These trends are occurring alongside rapid growth in the availability and consumption of commercially produced and packaged foods, including CCF.


Read the Healthy Starts 2026 report

While appropriately formulated and fortified CCF can play a positive role in young children’s diets, by providing essential nutrients in convenient forms, products high in sugar, salt, and unhealthy fats may displace more nutritious foods that children need for optimal growth and development.

Building on ATNi’s extensive research in Infant and Young Child Nutrition, assessing major manufacturers of breast-milk substitutes and CCF across markets, Healthy Starts provides a comprehensive assessment of the role of commercial complementary foods in young children’s diets, combining research on consumption, caregiver perceptions, markets and policies.


Objective

To understand the role of CCF in infants and young children’s diets in Kenya and Bangladesh amidst the growing CCF market.

To achieve this objective, the project addresses the following key research questions:

Consumption and perceptions

  • Which CCF and other commercial foods do young children consume? ​
  • What is their nutritional contribution to young children’s diets? ​
  • Why do caregivers choose, or avoid, these products?​
  • Are there differences between urban and rural settings and across socioeconomic groups?

Market and product landscape

  • What CCF products are available in the market?
  • Are these products healthy and responsibly marketed?

Local CCF production

  • What are the challenges and opportunities for local production of healthy, affordable, and accessible CCF?

Activities

In the first phase of the project, ATNi conducted a policy and market landscape analysis in Kenya and Bangladesh to understand the status and key determinants of infant and young child nutrition, the evolving CCF market, and relevant policies and guidelines. The analysis combined desk research with key informant interviews with local and global experts. The findings highlighted key evidence gaps and informed the design of the project’s subsequent research activities.

  1. 24-hour dietary recall to assess the contribution of commercial and home-prepared foods to the diets and nutrient intake of children aged 6-36 months in Kenya. (n=632)
  2. Focus group discussions and interviews with caregivers and healthcare professionals to understand complementary feeding practices, caregivers’ perceptions of commercial foods, and the factors shaping feeding decisions in Kenya (n=163) and Bangladesh (n=15).
  3. Assessment of 87 CCFs from 19 companies using the WHO Nutrient and Promotion Profiling Model to assess the nutritional quality, labelling practices, and pricing of locally produced and imported CCF available in Kenya.
  4. Interviews with companies operating in Kenya and Bangladesh’s CCF market (n=9 and n=7) to understand industry practices, challenges, and opportunities in improving the availability of nutritious foods for young children.

The research activities were conducted between July 2025 and July 2026.

Commercial foods are increasingly part of young children's diets

In both Kenya and Bangladesh, home-prepared foods continue to provide the majority of children’s dietary energy and nutrient intake. Meanwhile, commercial foods, including packaged foods and foods purchased outside the home, were found to increasingly contribute to children’s energy intake in Kenya as they grow older, with higher contributions observed among lower-income households.

Read more about the Key Findings

Most commercial foods consumed in Kenya and Bangladesh were not CCFs, highlighting the need to look beyond CCFs alone when considering young children’s food environments. Commercial foods were generally perceived positively by caregivers in terms of convenience, healthiness, and nutritional value. Despite these perceived benefits, concerns about the safety and quality of commercial foods were widespread across both Kenya and Bangladesh, with caregivers expressing reservations about the ingredients and overall trustworthiness of some products, particularly locally produced brands.
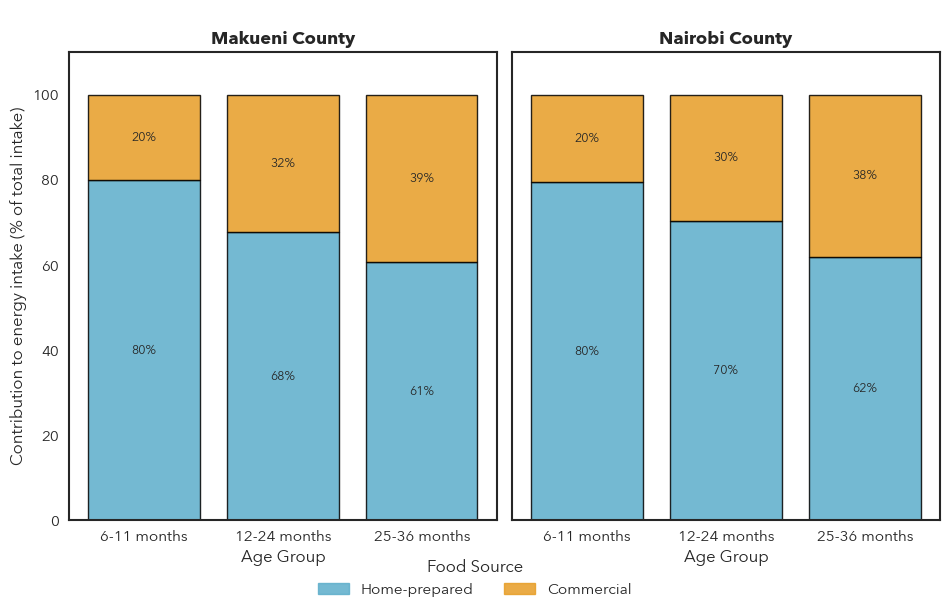
Figure: Contribution of home-prepared and commercial foods to total energy intake, by age group and county in Kenya (n=632)
Nutrition gaps persist despite adequate calorie intake

Most children in Kenya met energy requirements and several micronutrient needs from complementary foods, but protein and fat intake remained insufficient across all age groups. Diets were dominated by starchy staples such as ugali and porridge, while nutrient-dense foods, especially animal-source foods, were often limited by affordability and feeding practices.

Similar patterns were reported in Bangladesh, where protein-rich foods such as fish and meat were often unaffordable for low-income households, which relied more heavily on semolina and rice-based dishes with lentils.


Commercial complementary foods have potential but need improvement

Among 87 CCF products assessed in Kenya:

  • 46% met all WHO nutrient composition requirements.
  • The majority met fat (100%), protein (91%), and sodium (85%) requirements.
  • Only 62% met energy-density requirements.
  • 59% would require a front-of-pack high sugar warning label.
  • None met all WHO labelling requirements.
  • Breastfeeding messages were largely absent, while nutrition claims (e.g. “no added sugar”) appeared on 95% of products.
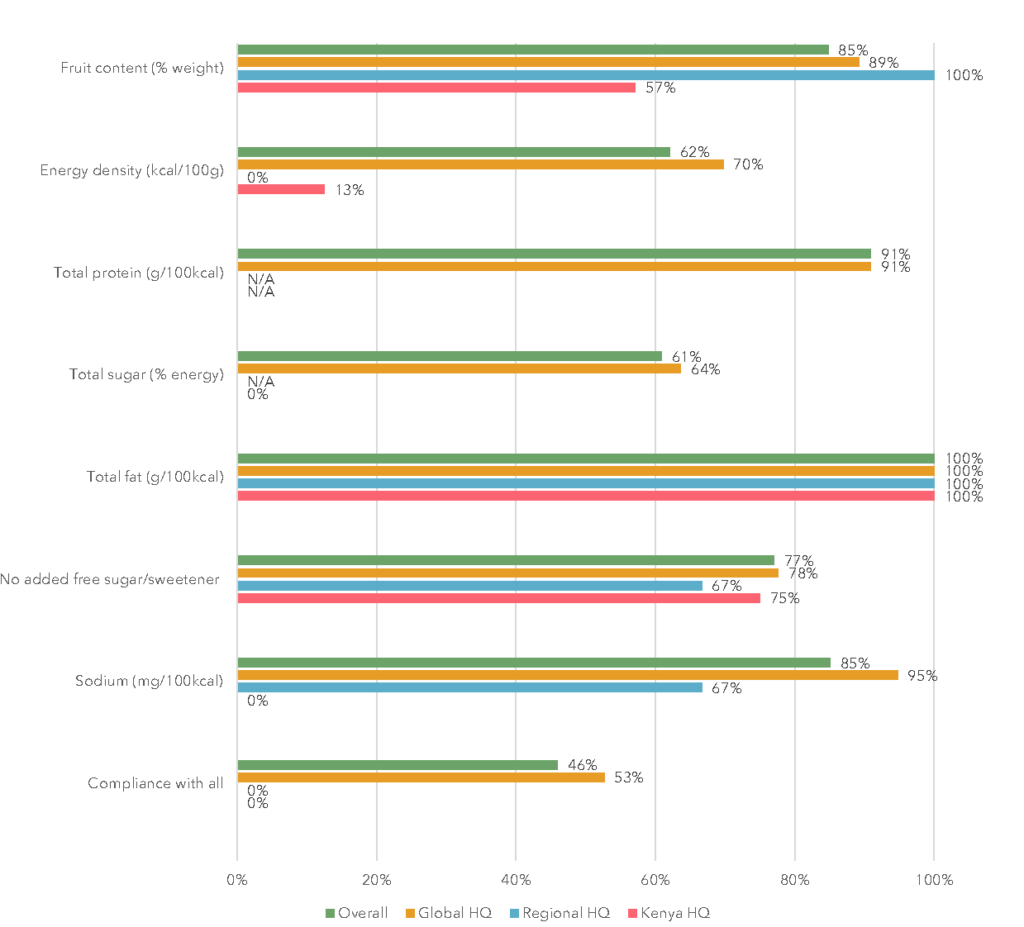
Figure: Nutrient requirements met, by company headquarters in Kenya
High sugar consumption is widespread

74% of children in Kenya consumed added sugars, primarily through sweetened porridge and tea. More than 60% consumed sweet foods, sweetened beverages, and/or salty and fried foods. Commercial products were the main source of these foods, particularly among children aged 12-36 months. Sweet foods were consumed almost exclusively from commercial sources, including packaged sweets, biscuits and cakes.

A similar pattern was reported in Bangladesh, with unhealthy food consumption increasing with age, with sweets and sweetened beverages being most common, and sugar often added to improve palatability. Common concerns regarding CCFs in Bangladesh included added sugars and minimal preparation guidance, while some CCFs in Kenya encouraged adding sugar during preparation or provided instructions that could dilute nutrient content.

Read more about the Key Findings

Local manufacturers have an important opportunity

Bangladesh has seen rapid market growth and increasing CCF sales through informal and semi-formal channels. Kenyan manufacturers account for more than half of identified CCF companies but represent a relatively small proportion of products in the market. In both countries, local products are generally more affordable and accessible than imported alternatives, but manufacturers face challenges related to limited access to finance, fortification costs, nutrient testing, product registration, and balancing affordability with nutritional quality.

While more than half of the CCF assessed in Kenya from global manufacturers met all WHO nutrient composition requirements, none of the local or regional products assessed did. Interviews with local companies, however, highlighted ongoing efforts in both Kenya and Bangladesh to improve nutritional quality through a range of approaches including fortification, biofortification (e.g. high iron beans) and protein enrichment.

Diverse home-prepared and traditional diets, alongside continued breastfeeding, should remain the foundation of complementary feeding. At the same time, improvements in commercial food products and food environments can support healthier infant and young child feeding practices. Achieving this will require coordinated action from industry, government, investors and development partners:

Companies

Companies should improve the nutritional quality, labelling, and responsible marketing of commercial foods, including CCF, in line with national standards and guidelines and the latest WHO recommendations.

Investors

Investors should integrate nutrition considerations into investment decision-making to maximise positive child nutrition outcomes and minimise nutrition-related risks.

Governments

Governments can strengthen enforcement and update national regulations governing commercial foods, including CCF composition and labelling standards, to cover products marketed for children aged 6-36 months and align them with the latest WHO recommendations.

Civil society

Civil society can support local manufacturers in producing affordable, nutritious foods for young children through technical assistance and access to finance.

Acknowledgments

The Healthy Starts 2026 project was developed by ATNi’s project team: Marina Plyta, Nadine Nasser, Lucy Cosenza, Irene Santoro, Ludovica Ibba, Kaitlyn Elavaza, Rachel Nel, Veronica Maxey, Valda Rahima, Freddie von Kaufmann, Elena Schmider, and Daniela Hernández Morales with oversight from Greg Garrett, Mark Wijne, Katherine Pittore, Sameea Sheikh, and Efi Chatzinikolaou.

ATNi would like to thank Dr. Juliana Kiio (Kenyatta University) for her support and oversight of data collection in Kenya, along with the team of enumerators, including Grace Waweru, Celestina Mutai, Faith Lagat, Gertrude Muchiri, Jacqeuline Macharia, Lydia Amoke, Mary Kyalo, and Neema Mbulwa,and the community health promoters who supported the fieldwork. We also thank Alliance Bioversity International-CIAT for their support with the dietary recall data collection tool; Dr. Shiksha Adhikari for her support with the dietary intake analysis; and ThirdWay Partners for their support with the company interviews in Kenya.

ATNi would also like to thank Bopinc for their support with the interviews in Bangladesh with caregivers, healthcare professionals and companies.

Finally, our sincere gratitude to the caregivers and healthcare professionals in Kenya and Bangladesh who participated in the research, as well as the companies, experts, and organisations interviewed for generously sharing their time and insights, which were invaluable to the development and successful completion of this research.

The Healthy Starts project is funded by the Children’s Investment Fund Foundation.

Contact Information

For more information linked to the project, please reach out to:  

Marina Plyta: marina.plyta@atni.org

email dropdown linkedin facebook twitter icon_input-select BMS Close Download Hamburger Performance Pijl Plus Product-Profile Share google-doc-tracking-XL Performance comparison-tool egagement-tracker-tool